

Toddler night wakings can be a particularly trying experience for parents, often characterized by prolonged crying that is more difficult to soothe than infant awakenings and more complex to reassure than those of older children. A primary culprit behind these nocturnal disturbances, affecting infants, toddlers, and even older children, is the presence of inappropriate sleep onset associations. This common issue is amenable to behavioral interventions, often referred to as sleep training.
Consider the challenging scenario faced by the Smith household. Their 14-month-old son, Jimmy, has a nightly routine that has become a source of dread. Since infancy, his parents have consistently rocked him to sleep each evening around 8 PM before placing him in his crib. While they hope for a peaceful night, their relaxation is frequently interrupted. By 11 PM, just as they are settling into bed, Jimmy begins to cry. Rushing to his room, they attempt to calm him by rubbing his back, a ritual that offers only temporary respite. These awakenings recur every hour to hour and a half throughout the night. By the time Jimmy wakes for the day at 5:30 AM, he is irritable, and his parents are profoundly exhausted, often unable to manage a midday nap due to the preceding night’s sleep deprivation. Jimmy’s persistent night wakings are a clear manifestation of inappropriate sleep onset associations, a prevalent cause of frequent nighttime awakenings in toddlers.
It is crucial to acknowledge that a spectrum of other factors can contribute to crying and screaming at night in toddlers. Understanding these potential causes is essential for parents seeking to identify and address their child’s specific sleep challenges. Some children may experience a combination of these issues concurrently. When parents struggle to pinpoint the root cause of their child’s nighttime distress, consulting a pediatrician is always recommended.
Inappropriate Sleep Onset Associations: The Cycle of Dependence
The typical child exhibiting inappropriate sleep onset associations falls within the 6 to 36-month age range, though this can extend to younger or older children. These children require the presence of a caregiver to initiate sleep and consequently experience frequent awakenings throughout the night. While parents often perceive the awakenings as the primary problem, they are, in fact, a symptom of a deeper issue: the child has not yet developed the ability to fall asleep independently.
In essence, if a child requires parental presence to fall asleep at bedtime and subsequently needs that same presence to return to sleep during the night, a sleep onset association is likely at play. The solution lies in teaching the child to fall asleep independently, a process commonly known as sleep training.
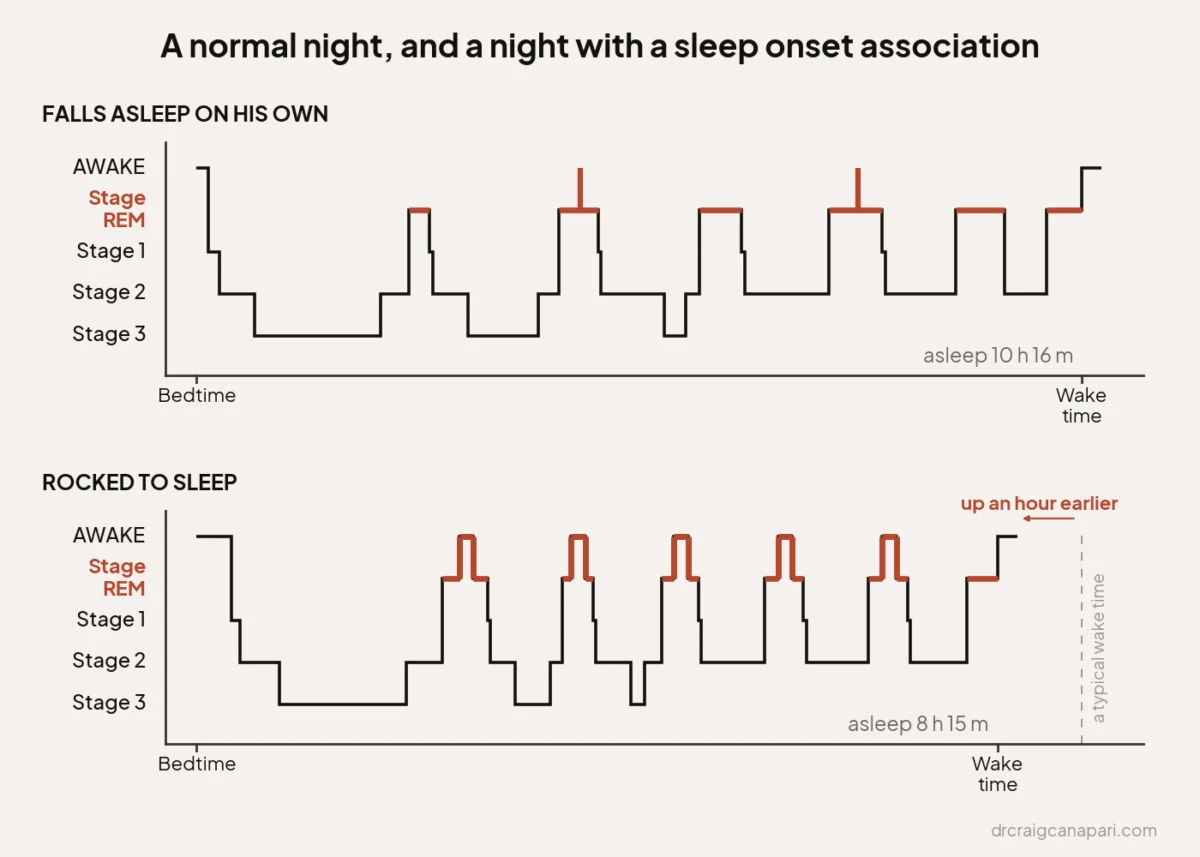
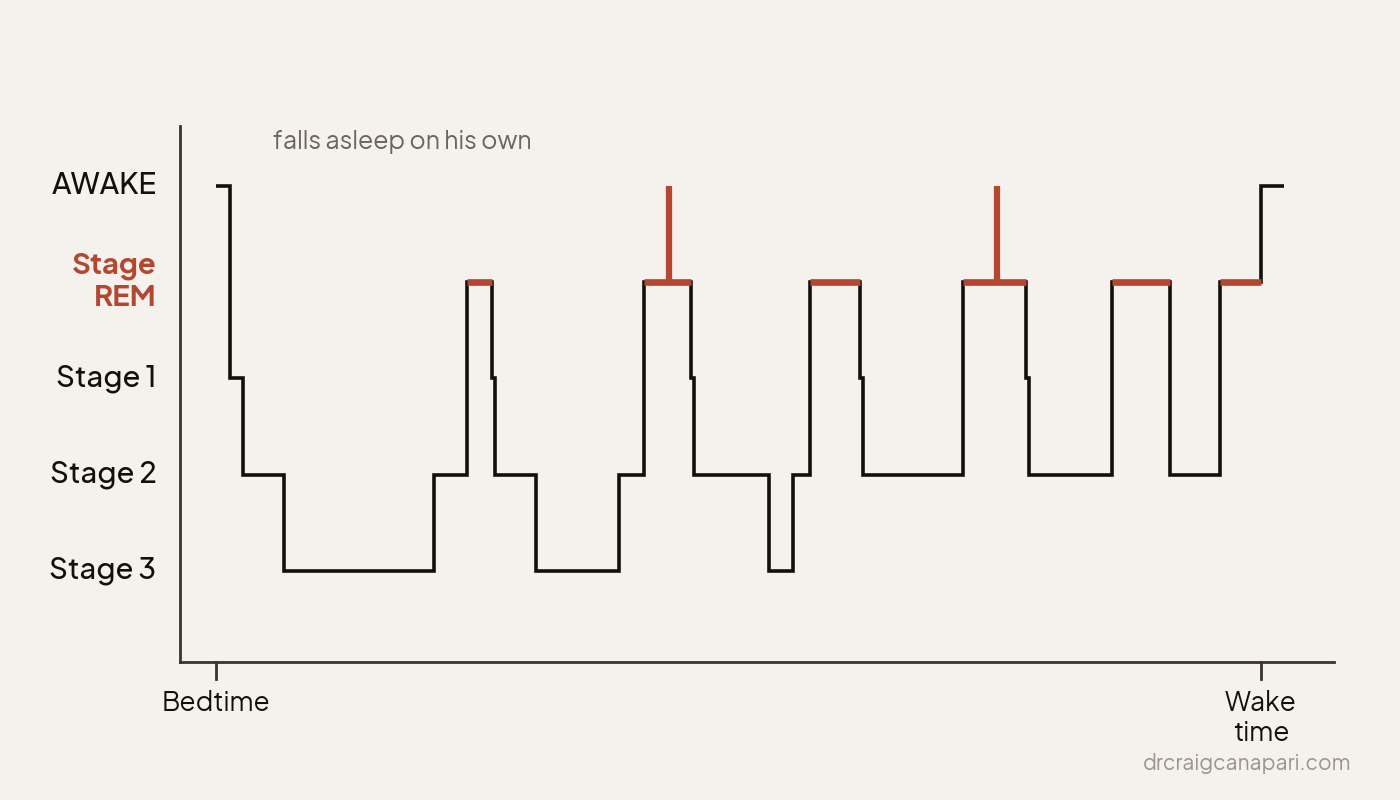
To illustrate this phenomenon, consider the concept of a normal night’s sleep, often depicted graphically as a hypnogram. This diagram illustrates the various sleep stages a child cycles through. Early in the night, a child typically enters deep, restorative sleep. As the night progresses, sleep cycles shift to include more REM (Rapid Eye Movement) or dream sleep. During these natural transitions, brief awakenings can occur. However, a child accustomed to falling asleep independently will generally not signal these awakenings to their parents, smoothly transitioning back into sleep.
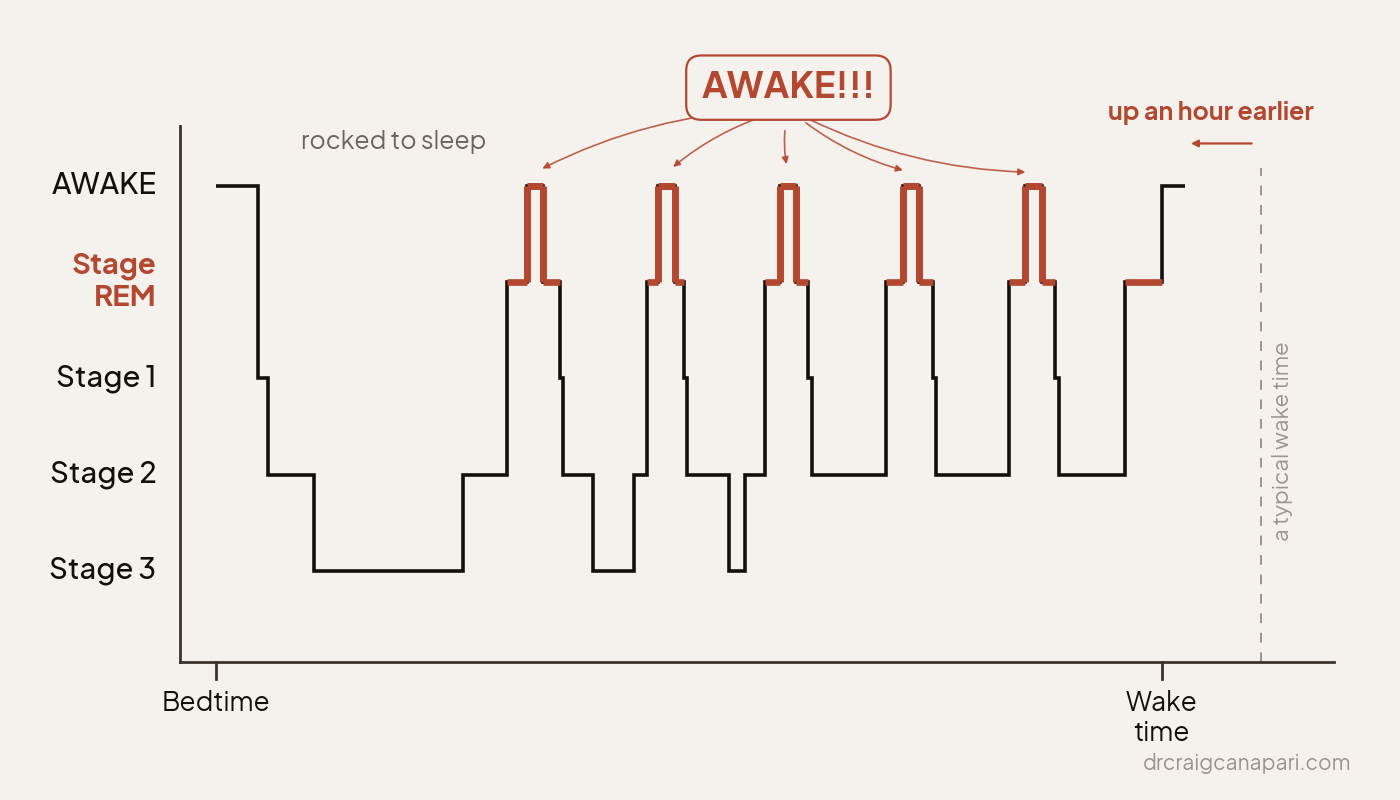
In contrast, a child who relies on parental assistance to fall asleep—whether through being held, rocked, nursed, or even pacified with a pacifier that may fall out—will seek those same conditions upon waking. For instance, if Jimmy falls asleep only when being rocked, he will likely require rocking each time he wakes during the night. This dependency can lead to a pattern of multiple awakenings and a reduction in overall sleep duration, often culminating in earlier morning wake-ups. This cycle can also inadvertently foster new sleep onset associations, such as co-sleeping, which can further complicate sleep patterns.
The technical classification of these sleep-related issues has evolved. Previously, they were categorized under "behavioral insomnia of childhood," with subtypes including sleep onset association disorder and limit setting disorder (characterized by "curtain calls" or repeated requests for parental attention). However, given the frequent overlap between these issues, particularly in children who have transitioned to a bed and exhibit sleep onset associations, they are now often grouped under the diagnosis of chronic insomnia, provided the symptoms have persisted for at least three months.
Night Terrors: A Different Kind of Awakening
Another significant cause of nighttime awakenings, often characterized by intense crying and screaming, is night terrors. These episodes are part of a group of disorders known as NREM parasomnias, which occur during non-REM sleep stages and manifest behaviors akin to wakefulness.
Night terrors are relatively common in toddlers, with studies indicating their prevalence can be as high as one-third of 18-month-olds, gradually decreasing to approximately one in five by age two and a half. Differentiating night terrors from sleep onset associations is generally straightforward. Night terrors occur during the deep, non-REM sleep stages, typically in the first half of the night, although they can occur later. Crucially, during a night terror, a child is inconsolable. Unlike sleep onset associations, where parental intervention can eventually lead to sleep, attempts to soothe a child experiencing a night terror are ineffective. These episodes can last from 10 to 40 minutes. While distressing, night terrors are usually not a nightly occurrence and often resolve on their own. The primary concern during a night terror is ensuring the child’s safety, as they may thrash about, though they typically remain in their crib or bed.
Temporary Disruptions to Good Sleepers
Several common life events can temporarily disrupt even a well-sleeping toddler’s routine, leading to night wakings. The key is to avoid inadvertently creating new sleep onset associations in response to these disruptions.
Sleep Regressions: Developmental Milestones and Disrupted Sleep
The term "sleep regression" is frequently used to describe periods when a previously good sleeper begins experiencing night wakings. While these disruptions are real, the notion of predictable, age-based regressions often promoted on social media lacks robust scientific backing. Research tracking night wakings over time indicates a general decline, with no distinct bumps at specific ages like 12, 18, or 24 months. However, significant developmental milestones, such as learning to walk or potty training, can be associated with short-term sleep disturbances.
The table below outlines common developmental phases and their potential impact on toddler sleep:
| Age | Parental Terminology | Underlying Developmental Factors |
|---|---|---|
| 12-15 months | "12-month regression" | Independent walking, pulling up, cruising. Transitioning from two naps to one may begin. |
| 15-18 months | "15- or 16-month regression" | Transition to a single nap (common between 12-24 months). Sharpening of separation awareness. Eruption of first molars. |
| 18-24 months | "18-month or 2-year regression" | Emergence of autonomy and limit-testing behaviors. Eruption of canines. Physical ability to climb out of the crib. |
| 2-3 years | "2-year or 2.5-year regression" | Transition from crib to bed (often due to climbing out or arrival of a new sibling). Potty training. Eruption of second molars. |
| 3-3.5 years | "3-year regression" | Nap cessation (commonly between 3-5 years). Total sleep needs decrease. Increased prominence of night fears. Start of preschool. |
Beyond these developmental leaps, other factors such as illness, travel, schedule changes, the arrival of a new sibling, or a household move can also temporarily disrupt sleep. The danger lies in the parental response; resorting to creating new sleep associations, like rocking a child back to sleep, can prolong the sleep disturbance.
Illness: A Temporary Setback
When a toddler is sick with a cold or fever, sleep disruption is a common consequence. Nasal congestion and ear pain can be exacerbated when lying down. During such times, providing comfort and care is paramount. However, parents should be mindful that if a sick child is consistently brought into the parent’s bed for extended periods, it can establish a new sleep onset association that may need to be addressed later.
Teething: A Misunderstood Culprit
Teething is frequently blamed for sleep problems, but its impact is generally limited to localized, mild, and brief irritability around the time a tooth emerges, typically lasting only a night or two. Teething does not cause fevers, although it may slightly elevate body temperature. If a child exhibits fever or appears unwell, attributing it solely to teething is ill-advised; medical consultation is warranted.
New Sibling Dynamics
The arrival of a new baby can disrupt a toddler’s sleep, especially if children share a room. A crying infant can awaken a toddler, making white noise machines a useful tool, provided they are used at an appropriate volume and placement. The stress of a new sibling can also impact sleep, though these disruptions are usually short-lived. Dedicating individual time to the toddler can help them feel secure during this significant family transition.
Medical Disorders: Underlying Causes of Persistent Wakefulness
Several common and chronic medical conditions can be overlooked as causes of sleep disruption. These are typically issues that occur multiple times per week or are associated with a known chronic condition. Persistent nighttime coughing, for example, could indicate asthma requiring treatment. Acid reflux can lead to nighttime abdominal pain and vomiting. Obstructive sleep apnea, often accompanied by snoring, is another common condition that can significantly disrupt sleep.
Schedule and Environmental Factors: Optimizing the Sleep Setting
Structural issues related to a child’s schedule or sleep environment can also be addressed to improve sleep.
Hunger and Night Feeds: Addressing Learned Hunger
Toddlers generally do not require nighttime feedings unless there is a specific medical reason. Weaning nighttime bottles or breastfeeding sessions can often lead to rapid improvements in sleep. Parents concerned about their child’s growth should consult a pediatrician.
Excessive Time in Bed: Adjusting Sleep Opportunities
"Too much time in bed syndrome" occurs when a child’s sleep schedule remains the same as when they were younger, even though their sleep needs have decreased. For instance, a child who slept 12 hours at age one may no longer require that much sleep at age three, especially if they are still napping. This can lead to them waking up during the night. Adjusting bedtime or considering dropping a nap may be necessary.
Environmental Disturbances: Optimizing the Sleep Space
Obvious environmental factors can also disrupt sleep. Electronic devices should be removed from the bedroom. Noise from neighbors or traffic, or a sibling who makes noise during sleep, can also be problematic. Room sharing with siblings can amplify night wakings, as one child’s disturbance can often wake the other.
In Summary
Toddler night wakings are a common and challenging aspect of parenting. For children who rely on parental assistance to fall asleep, sleep training can empower them to sleep through the night, offering relief to both child and parents. When children fall asleep independently, identifying and addressing other potential causes, such as developmental milestones, illness, or environmental factors, is key. By understanding the diverse range of factors that can contribute to night wakings, parents can more effectively navigate these challenges and foster healthy sleep habits for their children.
Originally published September 2026. Last reviewed/updated by Dr. Craig Canapari, MD in September 2026.
